Chat with us, powered by LiveChat
PMWC Overview Videos
Co Hosts
15-Track, 3-Day, Leading Precision Medicine Agenda
Largest & Original Forum for Precision Medicine
15-Track, 3-Day, Leading Precision Medicine Agenda
Facilitating Collaboration in the Field of Personalized Patient Care
The Largest & Original (Est. 2009) Forum for Precision Medicine
Facilitating Collaboration in the Field of Personalized Patient Care
The Largest & Original (Est. 2009) Forum for Precision Medicine
15-Track, 3-Day, Leading Precision Medicine Agenda
Facilitating Collaboration in the Field of Personalized Patient Care
15-Track, 3-Day, Leading Precision Medicine Agenda
The Largest & Original (Est. 2009) Forum for Precision Medicine
Facilitating Collaboration in the Field of Personalized Patient Care
The Largest & Original (Est. 2009) Forum for Precision Medicine
15-Track, 3-Day, Leading Precision Medicine Agenda
The Largest & Original (Est. 2009) Forum for Precision Medicine
15-Track, 3-Day, Leading Precision Medicine Agenda
Facilitating Collaboration in the Field of Personalized Patient Care
15-Track, 3-Day, 400-Speaker Precision Medicine Agenda

SPEAKERS / HONOREES

 -Select:

PMWC 2027 PIONEER HONOREE
BRCA1 Discovery Pioneer

PMWC 2027 LUMINARY HONOREE

2024 Nobel Laureate

PMWC 2027 J. CRAIG VENTER VISIONARY HONOREE

Nobel Laureate (CRISPR)

PMWC 2027 PIONEER HONOREE
2025 Breakthrough Prize (GLP-1)

PMWC 2027 PIONEER HONOREE

Nobel Laureate

PMWC 2027 PIONEER HONOREE

Godmother of AI

 

PMWC 2027 PIONEER HONOREE

Nobel Laureate

PMWC 2027 LUMINARY HONOREE

Google Brain Founder
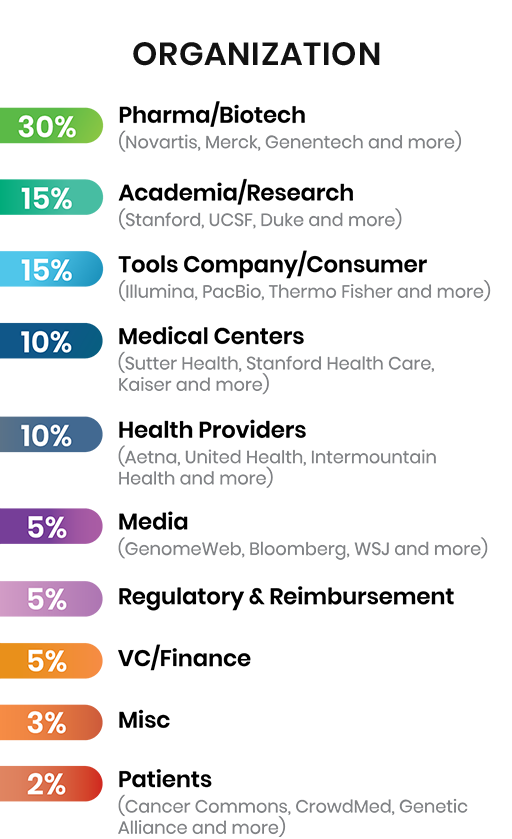
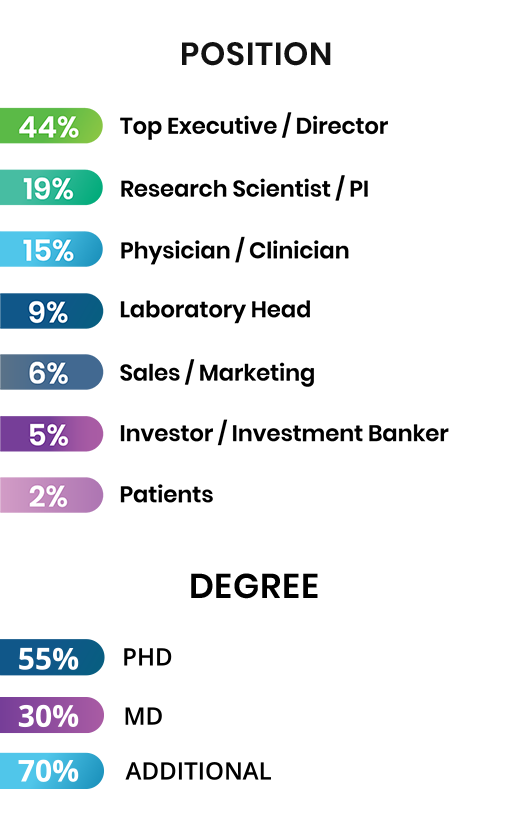
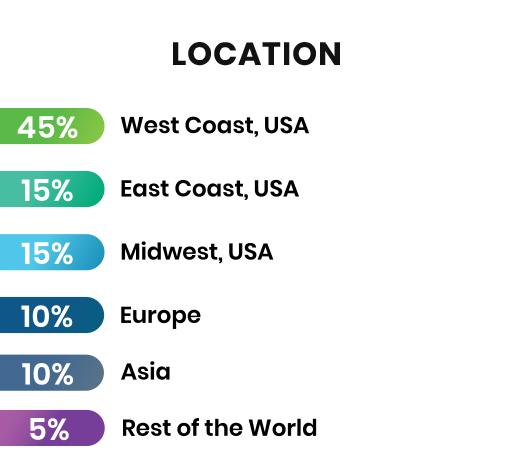
Bringing Together

DAYS

ATTENDEES (35 COUNTRIES)

EXHIBITORS

PARALLEL TRACKS

Format

The conference format consists of five parallel talks spanning 3 full days. Main Tracks 1-4 include sessions by leaders in the commercial, pharmaceutical, academic, government, regulatory, venture capital, and non-profit arenas that deliver a broad and up-to-date array of content across the various facets of precision medicine. Session discussions focus on time-relevant aspects with a selected set of key stakeholders, while commercial sessions cover the latest developments in technologies that are instrumental for the success of further adoption of precision medicine.

Additional 2 Tracks, feature Showcases: companies and research institutions can promote their platforms, launch products, and share research developments to a targeted audience – Apply.

For over a decade, PMWC has recognized individuals who have played a significant role in transforming health care by advancing precision medicine in the clinic with the Luminary and Pioneer Awards. The honorees’ numerous technological and scientific contributions have expedited this transformation as demonstrated by the clinical adoption of precision medicine, and the ongoing introductions of novel clinical applications. For a deeper look into the fascinating achievements of our past awardees see the awards page.

Receive the latest news about the field of precision medicine, and the conference from Tal Behar, PMWC’s President:

Interview with Jeffrey Bluestone, PhD

The long road to teplizumab and what comes next in autoimmunity

UCSF Distinguished Professor Emeritus | Managing Director, Vie Ventures

PMWC 2027 Silicon Valley | Thursday, January 28 | Track 5: Precision Immunology: Autoimmune & Inflammatory Disease

Luminary Honoree Teplizumab & Type 1 Diabetes Tregs & Immune Tolerance

01

From Discovery to Patients: The long road to teplizumab

Bluestone traces the journey from the original anti-CD3 work through clinical setbacks, industry partnerships and eventual approval, then outlines what that experience means for the next generation of tolerance therapies.

Q1Your anti-CD3 work, carried into the clinic with Kevan Herold, took decades to reach patients as teplizumab. What kept you going through the setbacks, and what should the next wave of tolerance therapies learn from it?
A:

The setbacks were many over the 40 years of development. OKT3g1(Ala-Ala) was developed in 1986. They came down to three core issues: five different companies with varying degrees of commitment, poor clinical trial design, and lack of a champion in the industry.

The drug started as a collaboration with Ortho Pharmaceutical/J&J, built on the background of OKT3. The work involved two scientists, Bob Zivin and Linda Jolliffe, with humanization by John Adair at Celltech. Unfortunately, Ortho decided to give up monoclonal antibodies as therapeutics. Even after they acquired Centocor, there was no interest in moving forward.

This cost us 10 years, although I was able to get access to the drug and make product for early phase I studies and phase II trials supported by the Immune Tolerance Network, with support from NIAID and JDRF. Kevan Herold was essential, as he conducted the clinical trial.

We then licensed the drug to MacroGenics. They were very engaged and motivated to develop it. In partnership with Lilly, MacroGenics started a phase III trial in stage 3, or recent-onset, type 1 diabetes. At the same time, a second company, Tolerx, was developing a similar Fc receptor non-binding, low-toxicity anti-CD3 monoclonal antibody.

The competition led to a large, complex clinical trial that required 300 sites and 500 patients in multiple arms, including sites and patients in India and Eastern Europe. The trial failed to meet its primary endpoint, and Lilly immediately terminated the partnership. However, further post-hoc analysis suggested that the primary endpoint was met if the analysis was limited to US patients.

At that point, MacroGenics agreed to out-license teplizumab to another company or a new company. But, not being a business development person, I found it very difficult.

By a stroke of luck, I met Leni Ramos, a previous chief medical officer at the Immune Tolerance Network, in New Orleans. She was at a meeting with members of her leadership team from a new company, Provention Bio. I suggested they might be interested in teplizumab. After multiple meetings and a meeting of the minds with the CEO at MacroGenics, teplizumab was licensed to Provention Bio.

In the process of replicating the phase III trial, data became available from a stage 2, "prevention" trial conducted by TrialNet, a consortium supported by NIDDK. The results showed that teplizumab could delay disease onset in high-risk stage 2 patients for two to three years. These data led to the approval of teplizumab in November 2022, some 35 years after development.

More recently, the results of the stage 3 new-onset trial led to a label expansion for this population, making the drug available to more people with early-stage disease or a recent diagnosis.¹

As for the next wave, this was the first disease-modifying immunotherapy for type 1 diabetes. In many ways, it has opened the floodgates. Approaches include novel anti-CD3 monoclonal antibodies, in one case given intranasally; antigen-based peptide therapies; antibodies against novel targets such as CD40L; and potentially tolerogenic cell therapies, including CAR- and TCR-Tregs and CD19 CAR-T cells.

02

Making Treg Therapies Accessible: Manufacturing, delivery and investment

More efficient manufacturing, potential allogeneic approaches and in vivo strategies could help broaden access. Vie Ventures is looking beyond individual diseases to common autoimmune pathways.

Q2Your fellow Sonoma Biotherapeutics co-founder Fred Ramsdell shared the 2025 Nobel Prize for discoveries concerning immune tolerance. What will it take to deliver Treg therapies at scale, and what do you look for at Vie Ventures in the next generation of tolerance companies?
A:

Treg cell therapies are a new field, and there are many areas where these therapies can be improved to provide greater access. This includes the potential for allogeneic therapies, assuming the immunogenicity issue can be resolved; more efficient manufacturing using automation and shorter or more efficient culture conditions; and even the potential for in vivo gene therapy, using novel approaches to ensure that expression of the target receptor, CARs or TCRs, is limited to Tregs.

Vie Ventures is committed to supporting companies in the autoimmune and inflammatory space, including startups and companies with drug candidates that need resources to tackle autoimmunity. One key aspect is that we look for innovative therapies that tackle core pathobiological pathways likely to be shared by multiple autoimmune diseases, not unlike anti-CD3, Tregs and similar approaches. Tolerance remains the Holy Grail for these treatments, but Vie is not restricted to tolerogenic approaches.

03

Intervening Before Major Symptoms: What comes after type 1 diabetes?

Earlier diagnosis and intervention may be possible across multiple autoimmune diseases as biomarkers identify patients before major clinical manifestations.

Q3Type 1 diabetes now has staging, autoantibody screening and a therapy that can act before insulin dependence. Which autoimmune disease is next to follow that model, and what needs to be in place in biomarkers or trial design?
A:

Multiple autoimmune diseases are in the mix for early intervention, given recent data identifying patients with disease before major clinical manifestations. These include rheumatoid arthritis, celiac disease, autoimmune Addison's disease, systemic lupus erythematosus, systemic sclerosis and autoimmune thyroid disease.

PMWC 2027 | JANUARY 28

Meet Jeff at PMWC 2027

Thursday, January 28 | Track 5: Precision Immunology: Autoimmune & Inflammatory Disease

  • 9:00 AM Luminary Award ceremony
  • 11:00 AM Beyond Broad Immunosuppression: Tolerance, Tregs, and Disease Modification
  • 1:00 PM Turning Biomarkers on Their Head: What We Can Measure Before We Can Predict

January 27–29, 2027 | Santa Clara Convention Center

Co-hosted by Stanford, UCSF and Yale

¹ Editorial clarification: The 2026 US stage 3 indication covers patients aged 8–17 and delays the decline in endogenous insulin production; it received accelerated approval. The stage 2 indication includes patients aged 1 year and older. FDA prescribing information (June 2026).

Interview with Samir Hanash, MD Anderson Cancer Center

Samir Hanash, The University of Texas MD Anderson Cancer Center | PMWC 2027 Silicon Valley, Track 3, Day 1, Session 2: The End of One Size Fits All

Interview Personalized Cancer Screening Proteomics & AI

1

Beyond Age-Based Screening: Personalizing cancer detection around individual risk

Hanash argues that reducing cancer deaths starts with determining who is at risk and for which cancer. He points to blood-based risk assessment across nine common cancers as a way to personalize screening and potentially enable prevention.

Q1 You pursued blood-based cancer detection long before it became a major field. What did you see that others did not, and what still must happen before early detection meaningfully reduces cancer deaths?
A: It became clear that the foundation for reducing death due to cancer is to determine who is at risk and for which cancer. This allows for screening to be personalized based on risk. At present screening is largely based on age and for just a few common cancers. Determining an individual’s cancer risk based on a blood test like we have done for nine common cancers provides a real time assessment of risk to tailor screening accordingly. Determining risk also provides an opportunity for prevention like eventually with a cancer vaccine for which an individual is found to be at risk or other means.

2

When Is a Multi-Cancer Test Ready? Cancer-specific evidence and cost effectiveness

For broad clinical adoption, Hanash calls for test performance to be calibrated for each cancer type. Mortality reduction remains the ultimate goal, with cost effectiveness and potential health care savings also part of the evaluation.

Q2 Blood-based early detection must distinguish true early disease from biological noise while avoiding unnecessary downstream procedures. What evidence should the field require before a multi-cancer test is ready for broad clinical use?
A: The performance of the test has to be calibrated on a cancer type by cancer type basis. Because some cancers are more common than others, one size does not fit all. Although the ultimate benefit is mortality reduction, in addition to performance, cost effectiveness meaning health care costs saved through the implementation of the test have to be taken into account.

3

From Proteomics to Prevention: Integrating multi-omics and AI

Hanash sees proteomics as essential for characterizing proteins and their locations. As vast proteomic datasets are combined with other omics and individual characteristics, AI becomes critical to translating that complexity into useful discoveries.

Q3 You helped establish HUPO and have watched cancer proteomics mature over decades. Looking ahead, how do you see proteomics, other omics, and AI working together to shift cancer care from late diagnosis toward interception and prevention?
A: Proteomics, other omics and AI can contribute substantially to shifting cancer care. First proteomics is essential to identify forms of proteins and their subcellular locations whether for diagnostics or therapeutics At present with the advances in proteomics technologies from one biological sample terabytes and terabytes of data can be generated for discovery that can be incorporated with other omics data and with subject characteristics making the use of AI essential to derive the most benefit from such data.
Interview with Jay Bradner, M.D., Amgen

James “Jay” Bradner, M.D., Executive Vice President, Research and Development, Artificial Intelligence and Data, Amgen

Interview Drug Discovery & Chemical Biology AI & Data in R&D

1

Reaching the Undruggable Proteome: Molecular glues, degraders and what remains out of reach

Bradner describes how chemical biology, molecular glues and induced proximity are opening historically intractable targets, particularly in gene control. But intrinsically disordered proteins and the intracellular delivery of large biomolecules remain major challenges.

Q1 Much of the proteome was once considered undruggable. Molecular glues, degraders, and induced proximity have changed that premise. What can we reach today that was out of reach ten years ago, and what still feels out of reach?
A: The chemical biology mindset has contributed meaningful in-roads to the discovery of new molecules working in new ways, in many cases on historically intractable targets. Molecular glues, which remain a focus of my research, leverage large protein interfaces adjacent to binding sites to complete molecular recognition events, allowing the engagement of protein targets that would otherwise not be “druggable”. This has been particularly exciting in the field of gene control, which for years was the focus of my scholarship as an investigator. Gene control proteins, in particular transcription factors, frequently possess intrinsically disordered regions that rare adopt coherent secondary structures. High entropic penalties and absent binding sites continue to challenge the drug hunter. Beyond small molecules, approaches to deliver large biomolecules into cells remains a grand challenge, which we and others are working on to this day.

2

Where AI Is Changing Drug Development: From protein design to agentic workstreams

Bradner points to concrete AI applications across discovery, regulatory work and clinical development. His strongest near-term excitement is around agentic workstreams, while emphasizing that AI works best in the hands of disciplinary experts rather than as a substitute for them.

Q2 Your current role brings research, development, AI and data under one remit. Where is AI genuinely changing the probability of developing a successful medicine, and where is the field still mistaking hype for progress?
A: Artificial Intelligence is proving to be a powerful catalyst for biomedical discovery research and therapeutic development, with a growing number of high-impact applications. Protein structure prediction accelerates both de novo discovery of active large molecules, as well as their optimization for drug-like properties. Document authoring decreases the time to regulatory filing. Pattern recognition identifies new target pathways in complex genomic and phenotypic datasets. Forecasting and clustering optimize clinical trial enrollment. Together, these and other tools cut through complexity, improve decision-making and ultimately improve the probability of success. Most exciting to me at this moment is the systematic application of agentic workstreams to critical phases of pharmaceutical science, and business. AI is an instrument best played by a disciplinary expert, who has accepted the invitation to approach their work in a new way. While there remains some distracting hype around AI across sectors, there is no question that AI is emerging as a powerful adjacency for biomedicine – which we call convergent innovation.

3

What JQ1 Taught Us: Open chemical probes can accelerate an entire field

The JQ1 experience became a case study in how an openly shared chemical probe can accelerate biology far beyond its original hypothesis. Bradner traces its impact from BRD4 biology to protein degradation, oncogenic transcription factors and therapeutics now in clinical development.

Q3 JQ1 became one of the most widely shared chemical probes in modern biology, yet BET inhibitors have proven difficult to convert into approved medicines. What did that teach you about the distance between a beautiful hypothesis and a drug — and about how openly discovery should be shared?
A: In this post-genomic era, biomedicine is best practiced by hypothesis-testing. Where available, incisive prototype drugs paired with predictive pre-clinical models can expedite therapeutic translation. The experience of creating, characterizing, studying and sharing the BET bromodomain inhibitor, JQ1, provided a powerful learning. Open access to chemical probes opens up a field of study and accelerates medical progress. In the few years following the publication of JQ1, hundreds of laboratories worked with the molecule to learn about the biology of BRD4 in cancer, heart disease, fibrosis, inflammation, fertility, and most importantly the fundamental role of BRD4 in gene control (transcription elongation). In this way, JQ1 powerfully accelerated scientific discovery, bringing BRD4 biology into view in many disparate fields of study. Years later, scientists have used JQ1 as a work-horse of protein degradation, since our publication of the chemical solution to protein degradation and the molecule dBET1. Others have used JQ1 to recruit BRD4 to oncogenic transcription factors, such as the Androgen Receptor (at Halda, now J&J). JQ1-derived therapeutics are presently in advanced stages of clinical investigation as cancer therapies and for cardiovascular disease. I am hopeful that patients will benefit from the learnings of this remarkable molecule.

#PMWC27

Follow PMWC on these social networks

#PMWC27
Follow PMWC on these social networks

×

Add Names/PO on Receipt

Discover What's Next in Precision Medicine!

Join our community today for the latest news, exclusive interviews, and unique insights from world-renowned speakers and experts


Request Atul Butte Company Competition Submission Form

Fields marked with an * are required

Contact Us:

Fields marked with an * are required 

Save $1151 By OCT. 29
PMWC 2027 Jan. 27-29 • Santa Clara
15 tracks • 400 speakers Co-hosted by Stanford/UCSF/Yale • Davos of PM
SAVE $1151 Rate increases OCT. 29 LOCK IN RATE

Trouble Registering

Fields marked with an * are required

Stay Tuned For More Information.

Contact Us:

Fields marked with an * are required 

Sign up for occasional updates on upcoming conferences, news, and other information. 

Get Updates:

Submit to Speak in the PMWC Showcase

Fields marked with an * are required

Apply to Speak at PMWC Silicon Valley by NOV. 19TH

The PMWC team will reply back to a suitable company/topic with an official request for talk/speaker details.